


To Understand & be Understood
Tools to strengthen the prerequisites for talking about pain across languages and cultures.
Ishita Chawla & Martine Braathen
Service and interaction design
Diploma 2026
Nominated for AHO Awards
This is an exploratory project about the communication between general practitioners and women from ethnic minority backgrounds. Our interventions help strengthen the conditions for talking about pain across languages and cultures.
Pain is a subjective and complex experience that no one else can feel but yourself. The consultation with the general practitioner (GP) is therefore a particularly demanding context, where diffuse pain meets a system that requires concrete descriptions. Many people find that their GP doesn't truly see or hear them when they try to communicate their pain. This can lead to eroded trust, poorer treatment, and greater health inequalities
The project is grounded in the following brief:
How can we as designers create a more equitable dialogue when female patients with minority backgrounds communicate pain during GP consultations?
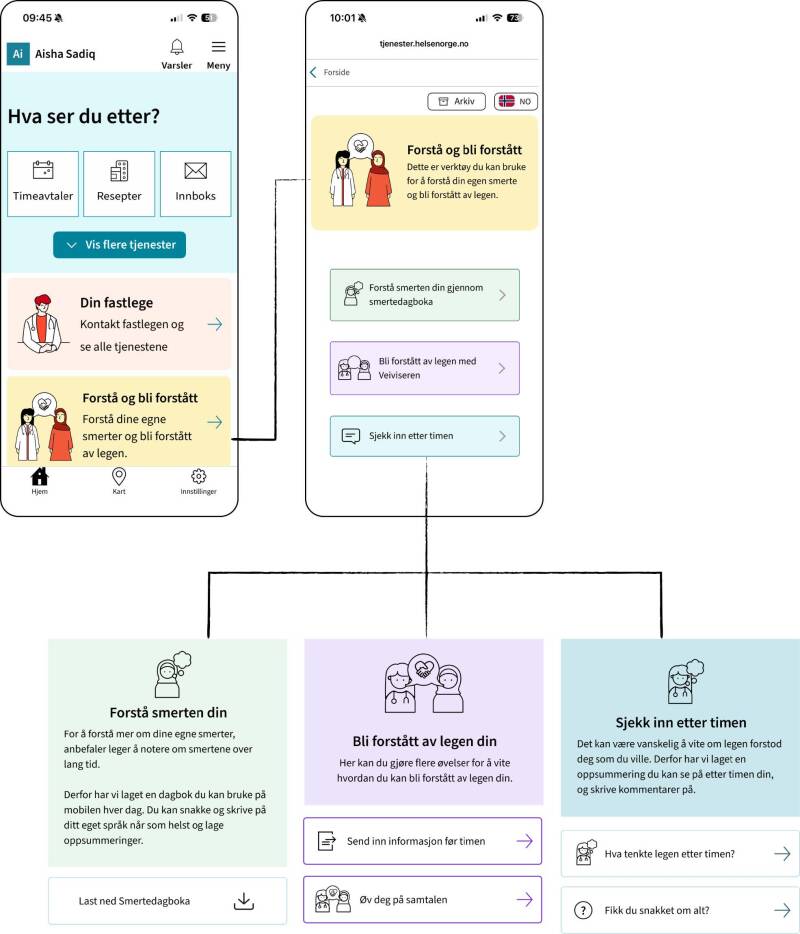
Based on three identified barriers, we have developed three digital tools that integrate into Helsenorge and are used before, during, and after the consultation:
Smertedagboken (The Pain Diary) gives women a low-threshold entry point for logging their pain and gaining an overview of connections and patterns over time.
Veiviseren (The Guide) functions as a framework to ensure that the appointment is spent on what matters most to the woman.
Sjekk-inn (Check-In) gives her the opportunity to reflect and flag any gaps or needs post consultation., and thereby take an active role in the ongoing dialogue with her GP.
Together, the tools shift the power balance in the consultation and make the patient an active participant in the conversation about her own health. By strengthening the conditions for communication, the GP gets a more complete picture of the patient's situation. The consultation becomes more precise, and the chances of an accurate assessment and treatment increase.
Listen to our diploma presentation here:
From research to design
We approached the project as an iterative service and interaction design process. We combined desktop research with interviews and user involvement to build an understanding of the experiences, needs, and challenges surrounding communication about pain.
We mapped the patient journey to identify where expectations, understandings, and communication between patient and GP diverged. This helped us move from individual experiences to broader patterns and identify the barriers with the greatest potential for design intervention.
From these insights, we generated ideas through a series of ideation exercises and explored different “what if” scenarios. We gradually narrowed these down into concepts, continuously asking how each idea could create value for both the woman and the GP.
We then moved between making, testing, and refining. Early concepts were concretised into prototypes and tested with users, allowing us to challenge our assumptions and adapt the solutions based on feedback. The process continued through several iterations before we selected and developed the final interventions.
Throughout the process, we worked with the tension between designing for a specific group and creating something that could be relevant beyond it. Rather than designing a solution to the healthcare system as a whole, we focused on the moments where design could make a concrete difference in the communication between patient and GP.


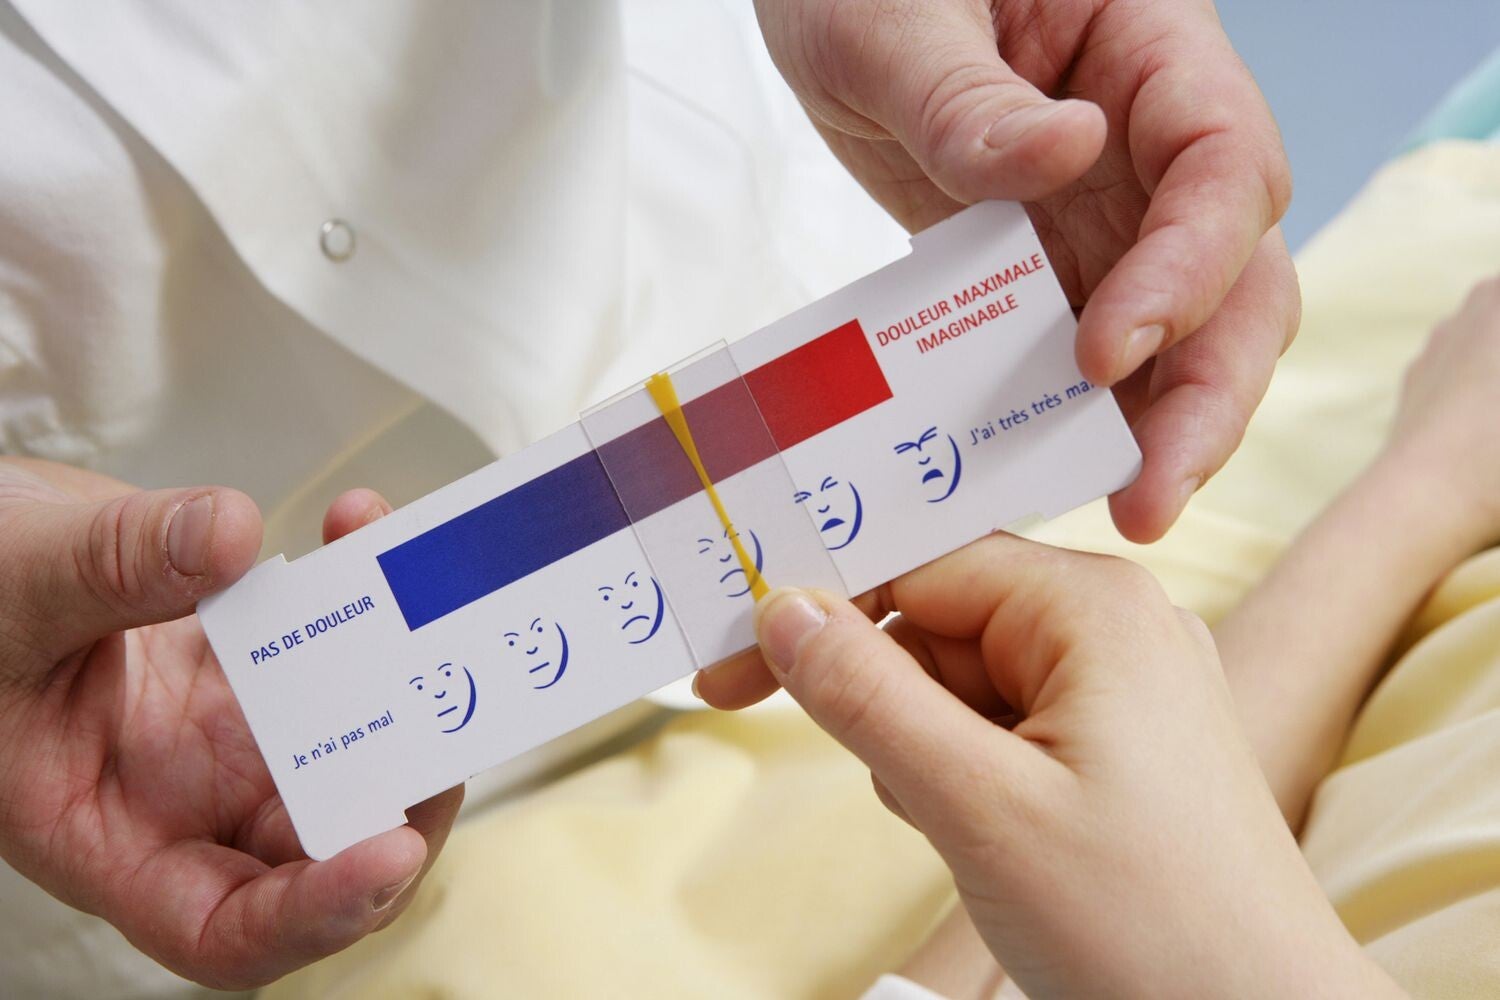

Current situation


Where do we start?
We wanted to focus on the communication between the patient and the doctor itself, rather than on the healthcare system as a whole. We quickly saw that these barriers pointed to concrete design opportunities that could make a real difference, while potentially contributing to larger systemic changes in the long term.
We then formulated three questions that shaped our ideation and the decisions we made moving forward:
1. How can we establish a foundation for mutual understanding between the expectations and needs of the patient and the doctor?
2. How can we strengthen women’s ability to talk about their pain when they come to a medical consultation?
3. And how can we create digital solutions that meet women where they are and provide tools tailored to their situation?
After several conversations with healthcare professionals and women about the ideas, we worked on categorizing the cards from the “What If” exercise based on what could work well together, what best addressed the brief, and what aligned with our three questions.
We conducted a total of five rounds of testing with different participants, including nine women from our target user group, three doctors, one medical student, one nurse, and one community mother.
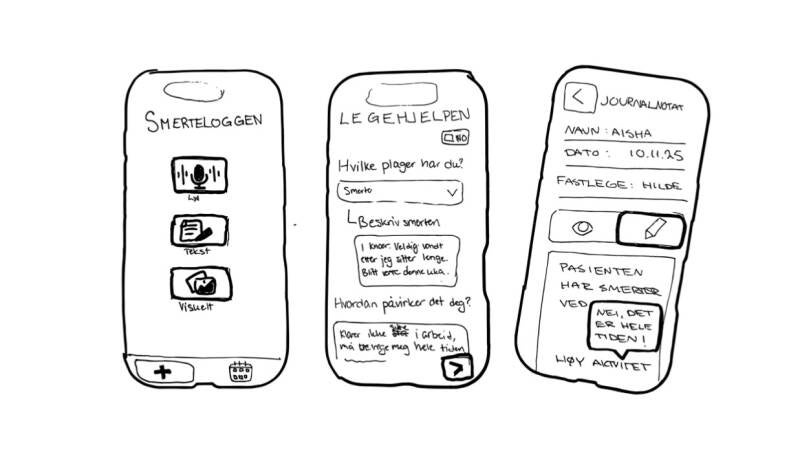
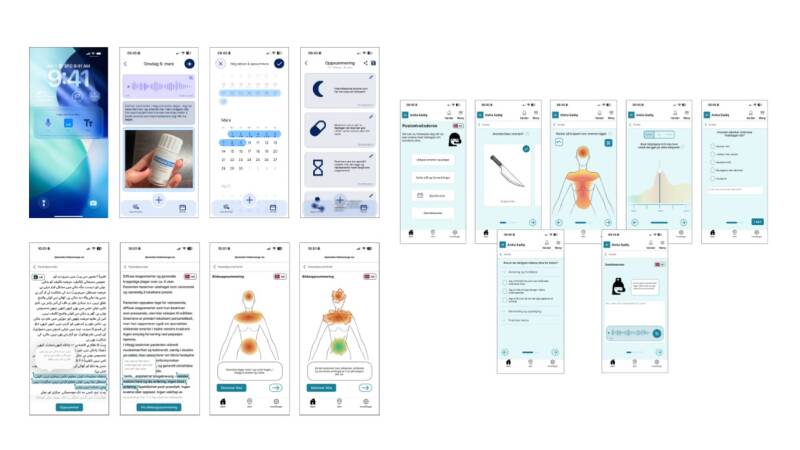
The prototypes were iterated between each round, evolving from hand-drawn sketches to digital prototypes and gradually into more interactive, clickable prototypes.

Our proposal
The service consists of three digital tools integrated into Helsenorge, designed to help users understand their own pain and feel understood when meeting their GP:
The first is Pain Diary, which helps users understand and track their pain.
The Guide creates a foundation for the consultation by helping the user communicate their experience and be better understood by the doctor.
Through Check-in, users can receive follow-up after the appointment and see whether the doctor understood them as they intended.
We chose to integrate the interventions into Helsenorge to create trust, credibility, and predictability. At the same time, we conducted a privacy risk assessment related to the Pain Diary. Since multiple people may have access to a patient’s profile in Helsenorge, it could feel like surveillance if a woman is unsure who can access her information. We therefore chose to keep the Pain Diary stored locally on the phone, while the summary is only retrieved directly by the doctor through Helsenorge.
AI is integrated into several of the tools we have developed. Considering the language barriers our target users may face, AI can help summarize and translate content across languages. By simplifying information and pre-filling forms, AI can lower the barrier to use by making it possible to communicate important information without requiring significant cognitive or emotional effort.
The three interventions are designed to work together, creating a continuous thread throughout the entire interaction with the GP.


This service blueprint visualizes how the service works in practice from both the patient’s and the system’s perspectives. It is divided into frontstage, backstage, and support processes, following the different stakeholders before, during, and after a consultation.
Overall, the service blueprint shows how the service creates better conditions for communication and mutual understanding throughout the consultation journey.





A special thanks to our supervisors,
Shivani Prakash
E-mail: shivani.prakash@designit.com
Erlend Grimeland
E-mail: Erlend.Grimeland@aho.no
...and, of course, to my partner throughout this diploma project,
Ishita Chawla
E-mail: ishita@hotmail.no

Address
Bjerregaards gate 21
Oslo, Norway
Socials